Dan, Heather, Jeremiah, Tory, Emma, Tye, Claire, Levi, Josie, Jane and Ethan

Friday, July 6, 2012

GSWs, Comfort and Doing the Right Thing


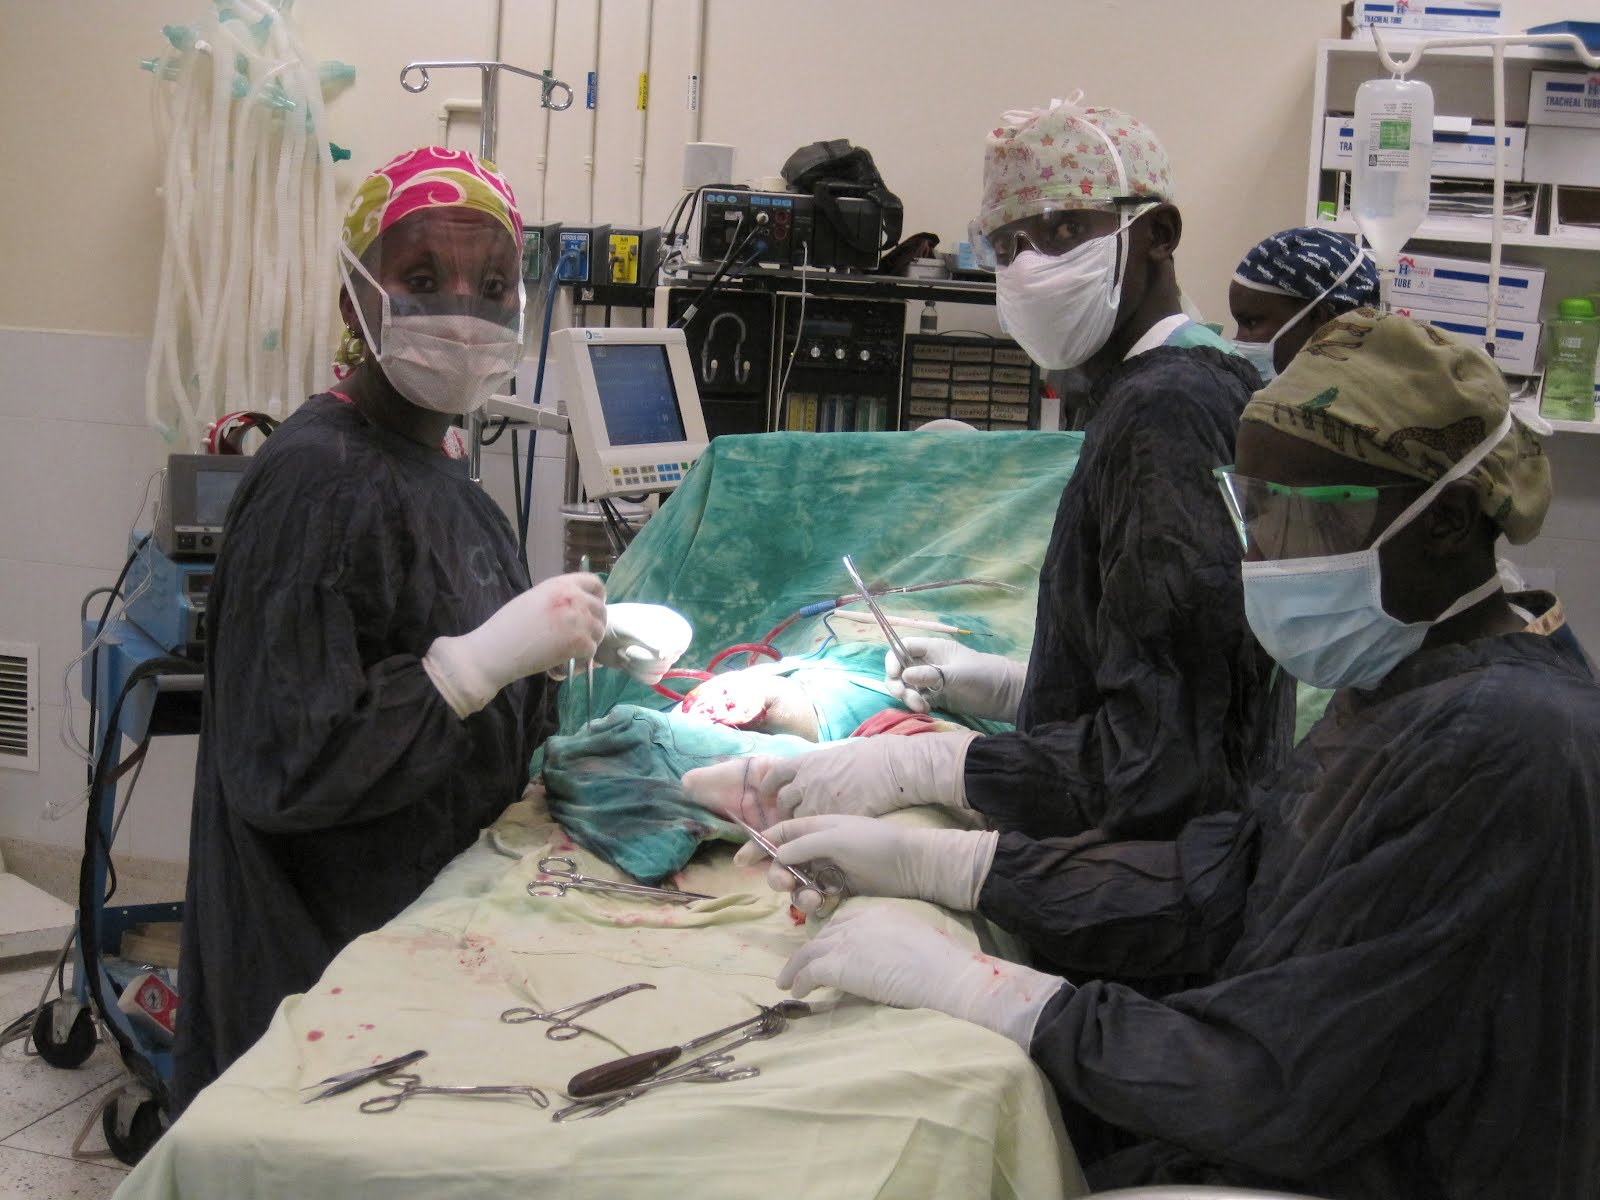
External fixator placed on the left leg helps keep leg aligned while the soft tissue and shattered bone heal. 


We were amazed at how well the bones were aligned despite not using C-ARM or x-ray in the operating room to assist.  Evidence that God was in control of this case.


The right leg fracture was not as severe, but the soft tissue injury was more extensive.  We were able to use a cast to hold this fracture in place.


Last Saturday evening, Heather and I had just settled down in front of a perfect fire, prepared for a quiet evening at home after a long week of intensive language studies and surgery, when my pager went off.  I had almost forgotten I was on-call, and while walking to the phone, I determined to dispatch of this call quickly so that I might return to my respite.  The general surgery resident efficiently rattled off three cases that had already been handled by the on-call team.  A distal radius fracture had been reduced, a closed femur fracture had been admitted, and even an open tibia fracture, secondary to a boda-boda (motorcycle taxi) accident, had already gone to theatre and been “washed out.” 

“I love having good residents on call,” I thought to myself, assuming the resumption of my evening of comfort was imminent.  Then came the pièce de résistance, a universal phenomenon in which residents always “save the best for last.”  “One last patient I want to run by you,” said Liz.  “Go ahead,” I said slowly, trying to hide my reluctance, instinctively knowing what was coming.  “It is an 18 year old boy with gunshot wounds to both legs, with bilateral open tibia fractures.”  Gunshot wounds (GSW as they are called by trauma surgeons) can be very challenging injuries with significant soft tissue loss and shattered bones.  “The patient was already ‘washed out’ at another hospital in Kisii, but we are wondering if he needs to go back to surgery again tonight,” she said, as if almost curious to see what I would say.  For a moment, I almost caved and pushed the case until the next day.  But knowing the poor quality of treatment at certain other hospitals, and not wanting to dump more work on the already over-worked Dr. Rowe, I said “we better take him back tonight.”

It was almost midnight as I left my warm house into the chilly night, being technically “winter” here at Tenwek, a few clicks south the equator, with lows at night in the mid 40s.  While walking up to the hospital, I passed the night watchman who was bundled in a bonafide winter coat, replete with a fur-lined hood.  (I have seen toddlers here dressed in snow suits on 75 degree, perfectly sunny days, reinforcing the concept that “cold” is definitely a relative term).  “I must be becoming more Kenyan,” I thought to myself as a chill ran down my spine, forgetting what “cold” really is having spent five long winters in Minnesota during residency.  When I arrived in theatre, Liz told me the rest of the story.  “Apparently, some thugs broke into the boy’s family home and were slashing his father with a panga (machete).  While trying to protect his father, the boy was shot with a single bullet that passed through both legs, shattering both tibiae,” she said.  “Then the thugs ran.”  She continued, “He was taken to a small hospital in Kisii where both legs were “washed out” in theatre and splinted; he was then transferred to Tenwek for definitive care.”

 After the spinal anesthetic was given, we removed the make-shift splints which were placed at the other hospital, and discovered that both legs were still dirty, indicating that a good I&D had not truly been performed, and wounds hastily stitched with thick, braided suture.  The first task was to thoroughly wash both legs, which was no easy task for only two people (thus prompting a call for chief resident reinforcement).  After a full “prep and drape,” we extended the incisions on both legs, washed the wounds with several liters of normal saline, debrided the dead muscle and tissue, placed a fixator on the left leg, lined up the fractures as best as we could without C-ARM, miraculously closed all wounds with minimal tension, and placed a plaster splint on the right leg, all of which took a little over two hours.  It was one of those cases where we all felt Christ directing our hands, and sovereignly blessing the work.   As I walked home, passed the bundled guard, and entered my still-warm home, I thanked God for giving me the grace and strength to do the right thing for this young man, and set the right example for the residents and staff, despite my strong, fleshly, continuous, selfish desire to remain comfortable.    

This past week, I returned to language study, and today, went to the ward to check on this patient, only to discover that he had already been discharged from the hospital!  Please pray for God’s complete healing in this young man’s life: spiritually, mentally, emotionally and physically.  Thanks for all your prayers and support without which, the work here would be impossible! 

Col. 3:23-4 Whatever you do, work at it with all your heart, as working for the Lord, not for men, since you know that you will receive an inheritance from the Lord as a reward. It is the Lord Christ you are serving.

Saturday, June 16, 2012

Full-Circle


(Story told with permission from patient).

Whilst walking home from language class (our family has been engaged in full-time language study learning Kiswahili, one of the two official languages of Kenya, in an attempt to master a language that some call “easy” but which, [being over the age of 40], I call challenging, especially since in Kiswahili there are 8 nouns classes, each with their own “agreements” for corresponding verbs, adjectives, adverbs, linking words, etc.), I heard a voice call out my name: "Daktari Kalad!" (in the local Kipsigis language, the letter G is pronounced with a K, and the letter T with a D).  Quite tired and not too excited to engage in another lengthy conversation in which I attempt to use a little Kiswahili and the other speaker some broken English, I slowly turned wondering who I might encounter.  I saw a vaguely familiar, middle-aged woman who walked toward me with a slight right-sided limp.  “Do you remember me?” she said with a thick, local-vernacular accent.  Trying to buy some time while jogging my memory, yet being savvy enough to use a little deductive reasoning (i.e. noticing her limp), I said, “Yes, you were one of my patients, right?”  A big smile appeared on her face, and as she reminded me of her story, the memory of her accident slowly returned.
In December 2009, while returning with family members from a wedding in western Kenya, just a few days before Christmas, the matatu she was riding in, stuffed with 17 people, lost control, veered off the road, and rolled several times.  One family member died instantly, and several were injured badly, including Amy, who fractured her left femur and right hip.  The injured were taken to Tenwek and Amy underwent nailing of her left femur and ORIF of the right hip the day before Christmas.  Although she was in the hospital for several weeks after her surgery, like so many of our patients, at discharge, she disappeared, falling into the deep abyss that I call “lost to follow-up.”  Now, a little over two years from her injuries, she “reappears,” walking, looking healthy, and now very happy.  “May I come for a visit?” she asked without hesitation.  “You are welcome,” I responded, a little hesitant at what such a visit might bring, yet at the same time sensing God might have something in store.
 A few days later, Amy appeared at the worst time, as I had several workers at our house fixing problems related to electricity and the strong shocks we were receiving while washing dishes (?).   “Can you come back another time?” I asked, probably with a slight look of frustration related to the seemingly endless issues that accompany living in an old house.  “I will come back” she said without the least amount of disappointment, and limped off.  Two days later, she returned, this time with her youngest son, and since I now had time to sit and listen, she told me the rest of the story.  Amy is a tailor by trade, and her husband John had been a pastor with the local Africa Gospel Church.  For several years, they lived on a combined income of only 2000 Kenyan Shillings a month (about $30).  After her accident in 2009, hospital bills, combined with Amy's inability to work, pushed their family into deeper poverty.  To make matters worse, in January 2012, John lost his job pastoring his small church as the members were longer able to pay his salary, and, as a result, also had to drop out of bible school, being only one year from finishing.  What little they did have they were using to buy food. 
As we regularly have people stop by our house asking for food, school fees, and various other sorts of assistance, I was waiting for Amy to “drop the bomb” and ask for money.  However, she did not, and only said that she wanted to stop by to thank me personally for allowing God to use my hands to help her, and to simply ask for prayer.  I happy obliged, and while praying for God’s provision for this family, I felt that perhaps God was asking me to do more than just be her surgeon.  However, I have learned to be more cautious over the years (having been burnt several times) and first thought I should enquire into their situation with the local church to see is their need was truly legitimate.  After asking both pastors at our church about this young couple, they responded by saying, “Daktari, they have true need…if you can help them, please do.”
Long story short, our mission agency is allowing us to use funds from our Galat ministry account to provide the remainder of John’s tuition to finish his degree.  Our hope is that John and Amy will be able to continue in ministry, full-time, proclaiming to others all that God has done for them.  And we are privileged to be a part of their lives, as their story has returned to us, now full-circle after that initial meeting over two years ago in the Tenwek Casualty.  Thank you for partnering with us in this ministry that allows us to help patients like Amy and her family.  We appreciate your prayers and support!

Proverbs 22:2 Rich and poor have this in common: The Lord is the Maker of them all.

Friday, May 4, 2012

God is Able!


The Boy Can Run!
Paul Whiting, stellar orthopedic resident from Boston who rotated at Tenwek in March 2012, visited the home of Kipkoech, the boy with bilateral femur fractures and an open tibia fracture who was treated at Tenwek last November (for previous blog story, click Here).  Paul caught video of Kipkoech running just 4 months after his surgeries!  During the most recent follow-up visit, Susan, Kipkoech’s mother, told us that she did not believe that her boy would ever walk again (let alone run) and as a result of God’s healing work in her son’s life, she placed her faith in Christ and is now meeting weekly with Lori Rowe (Dr. Glen Rowe’s wife) to read and study the bible!

Claire’s Baptism


Our family recently returned from the Coast where we attended the annual WGM retreat.  We had a very refreshing time of rest, fun and spiritual growth…definite highlight for me was baptizing Claire in the Indian Ocean! 
Donated C-ARM on the Way!
Chicago C-ARMS, the company from which we purchased our latest C-ARM in 2010, is donating a second, newly refurbished C-ARM (same model) to Tenwek completely free of charge!  The owner relayed to me that his company was greatly struggling last year (as so many have been in the US).   He is a believer and regularly attends Willow Creek Church.  One Sunday, he was greatly impacted by a sermon his pastor, Bill Hybels, gave on tithing, biblical truths about managing money, and trusting God.  He felt God calling him to step out in faith BEFORE seeing God’s provision and committed the donation of this unit to Tenwek.  In the next two weeks after his email to me about this commitment, his company sold 4 additional units!  God delights in our simple faith!  The C-ARM is about ready to roll, but we are now trusting God to provide the finances to air freight the unit to Kenya.


Electronic X-rays for Theatre

Examples of the high quality x-rays now capable with our digital x-ray system at Tenwek.
When I returned to Tenwek last summer, I was surprised to find that we had transitioned to electronic x-ray viewing throughout Tenwek!  I was very skeptical at first, but this has turned out to be a HUGE blessing for us (e.g. no more hunting for lost x-rays AND image quality had increased exponentially).  Since we no longer print hardcopy x-rays, it is critical for our operating rooms to have computers with monitors in each room (especially for orthopedics).  Perhaps you would join Chicago C-ARMS by stepping out in faith to help us meet these two needs.  If so, send me an email (dgalat@gmail.com) and we can talk.  God is able!

Saturday, March 31, 2012

The Battle for Our Youth

Sunset over the Mara...view from Olderkesi.

The crew...

Pancakes and popcorn for breakfast...

Landcruiser races...only in Africa.

Not sure what this one was called, but the kids loved it.

Preparing for the hunt.

The result of the hunt.

More results...

Ouch.

The boys did a good job of slaughtering the goat (quicky and humanely for the PETA folks).

After the skinning...

Peter and the kidney...not fully sure he actually wants to do it.

The girls hovering over the chargrilled goat. Let's just say this goat was not the most tender specimen, although it tasted good...

Best part of the weekend...building relationships.

And time alone to learn and be with God.


Missionaries often carry varying responsibilities, one of our favorites being the MK (missionary kid) youth coordinators for our sending agency, World Gospel Mission (WGM) Kenya. So, this past weekend, Heather and I, along with fellow missionaries and friends Dino and Janice Crognale, Beth White, and Vera Steury took our junior high and high school MKs on a youth retreat to Olderkesi, a WGM development project in the heart of Maasai Land.

Significant events included a traditional Kenyan goat roast (Mbuzi Choma - chargrilled goat) which the kids themselves slaughtered, butchered and then heartily consumed. Peter White thoroughly impressed all by eating a raw kidney plucked directly from the freshly dispatched goat (although likely spurred on by the small wager I offered him to do so). Because the area around Olderkesi is known to have lions, leopards, Cape buffalo and more, later that same afternoon, the entire tribe went out hunting. Although nothing of significance was seen or bagged, the majority of the boys came back with long, sharp thorns piercing their ear lobes in classic Maasai fashion. Jeremiah unfortunately (“accidentally”) broke off the entire tip of a thorn in his ear lobe and is unable to retrieve it (what next?). Nighttime consisted of campfires, laughter, and general lack of sleep.

Although much fun was had, the focus of the retreat was definitely spiritual in nature. We led the kids through an incredible study in 2 Peter entitled “In the Last Days” which challenged us all to live with watchfulness, purpose, and passion, as our time on earth is short. I am humbled as I imagine what God is going to do with this bunch of regular, yet privileged kids in the future. At the same time, I realize that they are targeted by an enemy who employs false teachers and ideologies with the goal of leading them astray. For now, we were glad to be fighting with them this weekend and trust that God has given them “everything they need for life and godliness.” All our kids, whether here in Kenya, or in the U.S., are in a battle, and we need to fight with them and pray for them continually.

Thanks for all your prayers and support for us here in Kenya. Let's pray for our kids, that God would protect them, grow them, and ultimately raise them up as laborers in His kingdom, for His glory.

2 Peter 1:3: His divine power has given us everything we need for life and godliness through our knowledge of him who called us by his own glory and goodness.

Thursday, March 8, 2012

The God Who Sees: the Story of Achu

Daily dose of Achu's smile on morning rounds.

In the courtyard with Achu. She is still very emaciated but significantly more healthy since removing the piece of dead bone from her tibia.

Achu's sister accompanied her from Sudan to Tenwek and is with her all the time.

After removal of the dead bone...note the huge hole in her leg.

Achu is a beautiful, 15 year old Sudanese girl who presented to Tenwek with a huge piece of dead and infected bone sticking from her leg, the result of an injury which occurred a year ago. Because her mother was dead, and her father a drunk, Achu had no money, and no one to advocate for her care. So she became progressively more emaciated, and more hopeless as the infection grew worse. She prayed that God would somehow help her, and He answered by initiating a massive series of miraculous events that started in a hot and dusty clinic in South Sudan and ended at Tenwek hospital in Kenya (including sponsorship by Randy Alcorn's Eternal Perspective Ministries). For the full (and amazing) story, check out Kimberly Smith’s blog .

As our orthopedic team evaluated Achu, the foul smell of necrotic flesh was strong, and our first thought was "there is no way to save her leg." The piece of protruding bone was too large and after removing it, we were concerned that the remaining defect could never fill in with new and healthy bone. However, we were encouraged, as x-rays showed a surprisingly large bridge of new bone posteriorly, which explained why Achu, despite her condition, was still able to walk, bearing weight on her leg. In addition, we had the sense that God was at work and we were just along for the ride. So that same day, we took Achu to theatre, and removed this piece (approx. 3 inches) of dead sequestrum. Indeed, the hole it left in her leg was cavernous, but we could feel the bridge of bone posteriorly, and the leg miraculously felt very stable.

Achu is currently still in the hospital undergoing daily “whirlpool” therapy in a Jacuzzi-like tub to clear up any remaining signs of infection, and soon, we hope to continue wound VAC therapy which utilizes a sponge and suction to encourage formation of granulation tissue that will slowly fill in this defect. What is most striking to us now about Achu is her beautiful and continual smile, which, I believe, is the reflection of new found hope. She knows there is a God who has seen her condition and is loving her with a perfect love. Her story reminds me of Hagar, who when she met God, called him El Roi, "the God who sees me" (Genesis 16). God is answering her prayers (and the prayers of many others) and we are privileged to be a small part of this process, seeing yet another one of God’s miracles on behalf of the poor at Tenwek. I am humbled and moved to worship the Father who sees the neglected, the abused, and the hopeless.

Please pray for Achu, that she would continue to heal, and that God would powerfully use her testimony to touch the lives of many! Thanks for all your prayers and support!

(Hagar) gave this name to the Lord who spoke to her: “You are the God who sees me,” for she said, “I have now seen the One who sees me.” Genesis 16:13

Saturday, February 25, 2012

Never Neglected

Our current orthopedic team (actually minus a few people!).

Dr. Dama and Meshack, hard at work closing a wound at the end of a case.

"Bone transport" - something new at Tenwek. This patient had an open tibia fracture with a large bone defect of approximately 4cm. After "squaring off" the ends of the bone at the defect, a fresh cut was made in the bone further up toward the knee. Using this external fixator, the "free" bone segment will slowly be moved into the defect and new bone will fill in behind it, thus "transporting" the bone and closing the defect.

The defect will be filled with the transported segment of bone (at the rate of 1mm per day). Notice the cut in the bone proximally. As the bone is transported, new bone will fill in behind. Please pray for complete healing for this patient.

Neglected tibia fracture in a 5 year old boy who was seen initially at a large hospital in Nairobi. Unbelieveably, the boy was never even placed in a cast and developed this non-union. On Friday, we placed a small rod down the middle of the bone to stabilize it.


Early yesterday morning, while doing x-ray rounds with our orthopedic surgery team (incidentally the largest team we have ever had, a far cry from the “early days” when I first arrived in Kenya 2008 when it was only me and one female intern who had zero interest in orthopedics), the residents flashed the x-rays of a young Masai girl on the computer screen, which showed a huge mass about the knee. Given her age and x-ray findings of bony destruction and soft tissue swelling, the mass had all the characteristic looks of osteosarcoma, or bone cancer. Without even seeing the patient, it was clear to us all that the only treatment option for her, at this point, would be a high amputation near the hip.

Later that morning on patient rounds, our team met this little girl, and her condition was far worse than we anticipated. She was surrounded by a foul smell, her massive knee wrapped in a gauze dressing, as if in shameful attempt to hide what was underneath. Her hemoglobin was 3.0 (the lowest I have seen in a living patient), far off from the normal value of 15.0, and corroborated by the listless appearance of her dark-skinned, yet noticeably pale face. Blood needed to be given prior to any surgical intervention, otherwise she could easily die during the procedure.

After receiving blood overnight, the patient underwent surgery, which was performed by Dr. Adero, our visiting orthopedic resident from Moi University. After the leg was removed, we unwrapped the knee dressing in order to get tissue to send for pathologic confirmation of cancer. As we proceeded, we were all horrified by what we saw: the entire end of the femur bone was exposed (having slowly eroded through the skin as the tumor grew), with foul pus pouring from the knee. I needed to leave the room because I was nauseous, both from the smell, and from anger towards whoever allowed this poor girl to suffer so long, in such an inhumane way, before seeking any medical attention (aside from the multiple linear scars about the skin of the knee from the “medicine man” in a vain attempt to cure the problem).

As I reflect on this girl’s plight, and ask myself how any person could be so terribly neglected, I am reminded that while “man” (including parents, children, brother, sisters, best friends) may let us down, Jesus never will, even in the most challenging of circumstances. In fact, his care is so perfect that He can use anything we experience somehow for our good. My prayer for this girl is that in the midst of her suffering, abandonment and neglect, she might feel the deep love of her true Father, who will never leave her or forsake her, who will always be there, and, as a result, that she would trust Him with her life, however long she has left to live. May we all see this truth in our lives…God is with us…He sees what we are going through…He will never neglect.

Deut. 31:6 Be strong and courageous. Do not be afraid or terrified because of them, for the LORD your God goes with you; he will never leave you nor forsake you.”

Friday, February 3, 2012

“The Boy Can Walk”

Kipkoech (now a little over two months since surgery after having both femurs plated, and tibia casted) and his mother.

Kipkoech, walking quite well with crutches. His picture was also in the recent blog entitled "Hope."

Other young boys treated at Tenwek for lower extremity fractures. These three, whom we dubbed "the three musketeers" would daily join for wheelchair mayhem in the Tenwek courtyard.

All toothless smiles after being released from three weeks of traction for a femur fracture.


Last Wednesday, our busy clinic day, while walking across the courtyard from theatre to clinic, I heard a woman’s voice call out, “Dakarti, the boy can walk!” I turned and saw a nicely dressed, broadly smiling woman standing next to a young boy who was leaning on a pair of crutches. The boy looked very familiar, but I struggled to remember who he was of the several dozen young patients I had operated on in the last several months. I then recalled his story (and remembered that I had a picture of him in my recent blog entitled "Hope"). As is all too common in Kenya, while walking on the side of the road, he was hit by a car, and suffered bilateral femur fractures and a left compound (open) tibia fracture. After three surgeries, including plates and screws on both femurs, now only two months after his injury, he was walking quite well and x-rays showed that all his fractures were healing without any signs of infection.

After chatting with the boy and his mother for a while, the woman said, “Thank you for helping my boy walk again.” To be completely honest, when I heard this comment, I immediately felt a degree of pride, as if his ability to walk was somehow about me, and my ability. But then I remembered the entire orthopedic team (nurses, scrub techs, physiotherapists, etc.) that works so hard every day taking care of the many patients like Kipkoech...and I thought of the team of people all over the world who support the work at Tenwek through giving, encouragement and prayer...and I thought about the motto that has been Tenwek’s trademark for decades, “We treat, Jesus heals"...and finally, I was gently reminded by God where I would be without His amazing grace in my own life. I then had the overwhelming sense that all that happens here at Tenwek is NOT AT ALL about me, but rather about God’s unbelievable goodness and grace. I then told her, “Please give thanks to God, because he is the One healing your boy.” “Yes, of course,” she said shrugging her shoulders in Kenyan fashion...“I do!”

Thank you for partnering with us to help boys like Kipkoech walk again so that the name of Christ may be glorified!

Hebrews 12:12-13 Therefore, strengthen your feeble arms and weak knees. “Make level paths for your feet,” so that the lame may not be disabled, but rather healed.